
Diabetic Foot Ulcer Icd 10

A claim lands on my desk with three words in the assessment: “diabetic foot ulcer.” The wound photo shows a plantar lesion, the measurement says fat layer exposed, and the treatment includes sharp debridement and offloading. The coder still can't safely finish the claim because the note doesn't state the side, exact site, or diabetes […]
Braden Scale Calculator: How to Score and Use It Right

A 74-year-old patient is two days out from surgery. The Braden score looks moderate, so the admission checklist feels complete. But intake has worsened, the patient slides down in bed during transfers, and a Stage 2 pressure injury is beginning at the sacrum. The total score didn't change the fact that the patient's risk changed. […]
Wound Debridement: A Practical Guide for Clinicians
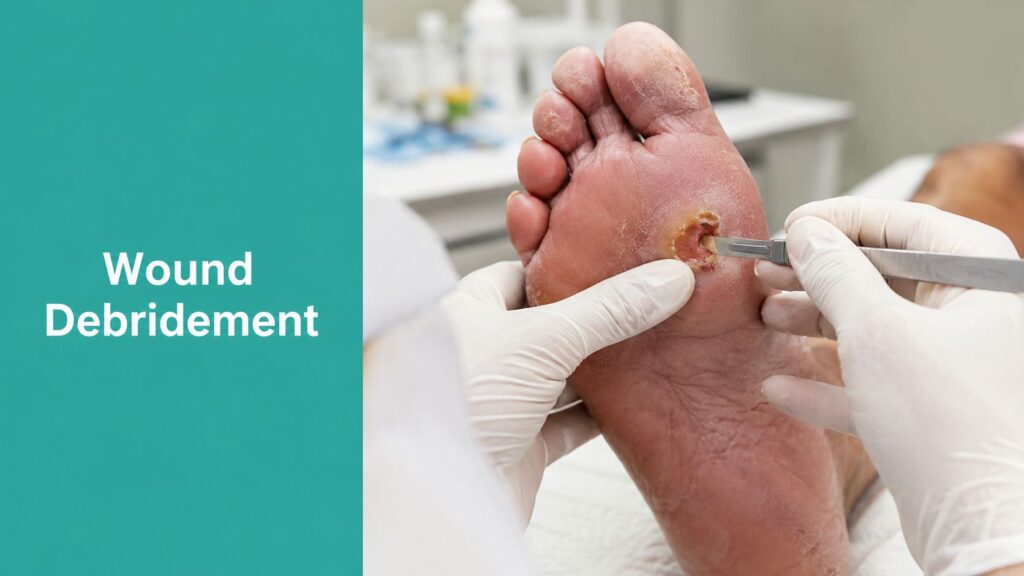
The plantar ulcer is open again, the callus rim is thick, and the dressing pulled away with a string of fibrinous slough. That's the moment when the room gets honest. The wound isn't choosing to heal on schedule, so the team has to choose the right sharp work, the right cadence, and the right note. […]
Selective Debridement CPT Code 97597 vs 11042-47
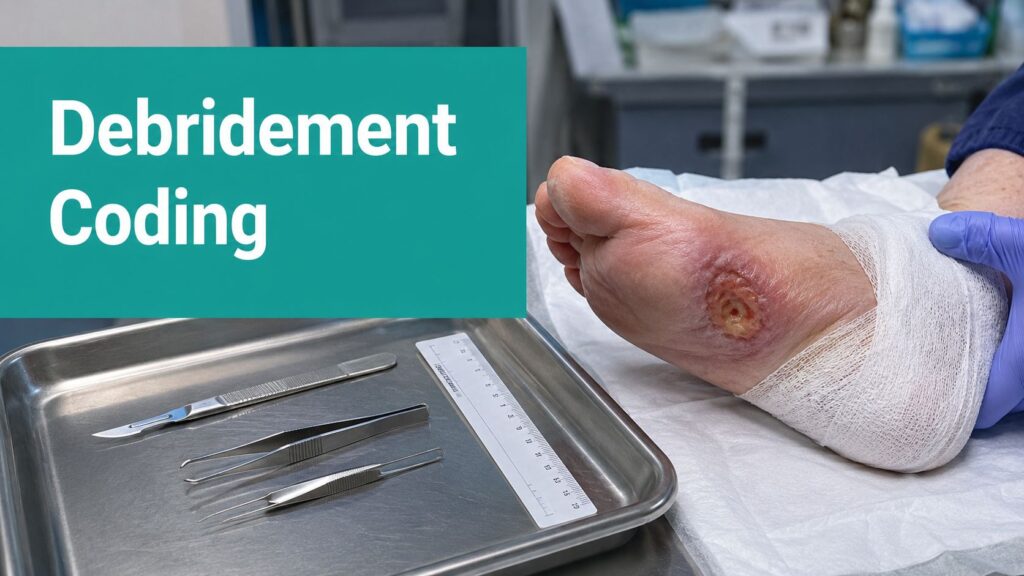
You debrided the wound correctly. The note looked solid. You documented slough, fibrin, serosanguinous drainage, healthy granulation after treatment, and the patient absolutely needed the work. Then the claim came back denied. That happens because wound care coding doesn't reward clinical intuition. It rewards documentation that matches the code set exactly. In practice, the biggest […]
Managing Redness Around Wound: Clinician’s 2026 Guide
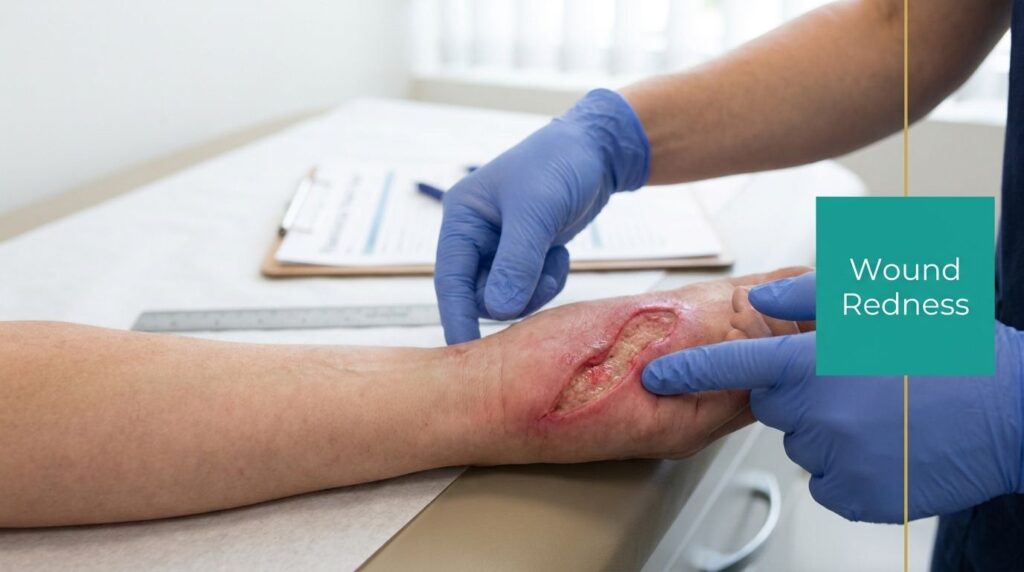
You're standing at the bedside with a chronic wound that looked stable last visit. Today there's a brighter red halo around it. The patient says it feels “a little hotter.” The nurse wrote “redness noted.” That's where people get into trouble. Some redness around wound edges is expected. Some is the first sign you're about […]
Unstageable Pressure Ulcer Guide for Clinicians
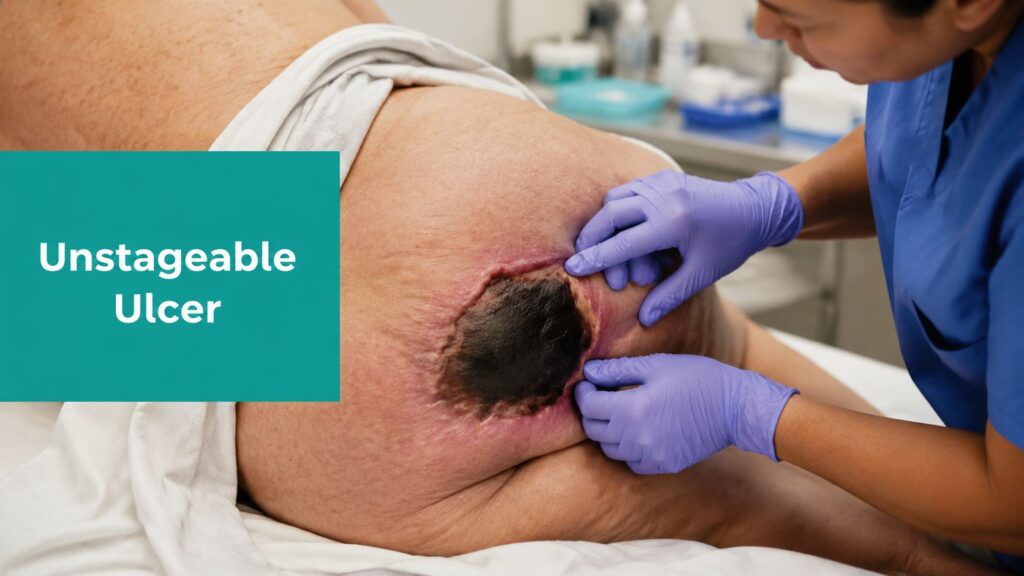
You get called for a “sacral wound,” and the chart already has the damage done. Someone typed “scab.” Someone else copied it forward. By the time the consult hits your list, the bedside problem has already become a coding problem. What you find is dry, black, leathery tissue over a pressure area. No one can […]
Expert Guide: 3rd Degree Burn Healing Stages 2026

Textbook wound-healing diagrams mislead people on full-thickness burns. If you start with inflammation, move neatly to proliferation, and end with remodeling, you've already skipped the event that determines whether this wound can close at all. A 3rd-degree burn doesn't “heal through stages” the way a superficial wound does. The clock is effectively stalled until the […]
Prior Authorization Software: Wound Care Efficiency

Friday at 4:20 p.m. is when prior authorization failures usually show up in wound care. The chart is done. The wound photos are in. The vascular history is somewhere in the note. The team is trying to get negative pressure wound therapy moving before the weekend, and the payer response comes back with the kind […]
Wound Care: A Clinician’s Guide to Never Events Healthcare

You admit a patient to the SNF on Friday afternoon. The discharge packet says “skin breakdown to sacrum.” That's it. No stage. No measurements. No wound photo. No note telling you whether the ulcer was present on admission, evolving, or already full-thickness. By the time your team gets a proper head-to-toe done, offloading started, and […]
Gradient Support Stockings: A Clinician’s Guide

The ulcer looked fine at discharge. Medial ankle, shallow base, granulating well after serial sharp debridement and compression wraps. A few months later the patient is back with the same leg, the same brawny edema, the same stasis skin changes, and a familiar line: “I've been wearing my stockings.” That's the moment when newer clinicians […]